14 November 2026
The Checkup You Keep Postponing After 40
Why "I feel fine" is not a plan
Most men who develop cardiovascular disease or type 2 diabetes in midlife felt completely normal in the years before diagnosis. Hypertension is famously silent; elevated LDL cholesterol builds plaque over decades without a single symptom. Prediabetes, the liminal state where blood sugar is higher than normal but not yet diabetic, typically produces no obvious signs until damage to small blood vessels has already begun.
This is the core argument for screening: it looks for risk factors that have not yet become problems. A man who feels fine and has a blood pressure of 148/94 is not fine—he is simply not yet symptomatic. The gap between those two things is where prevention lives.
The four numbers worth knowing
A thoughtful checkup after 40 does not need to be exhaustive. It needs to be consistent. These are the measurements that quietly drift in your forties, and the ones worth tracking over time.
1. Blood pressure
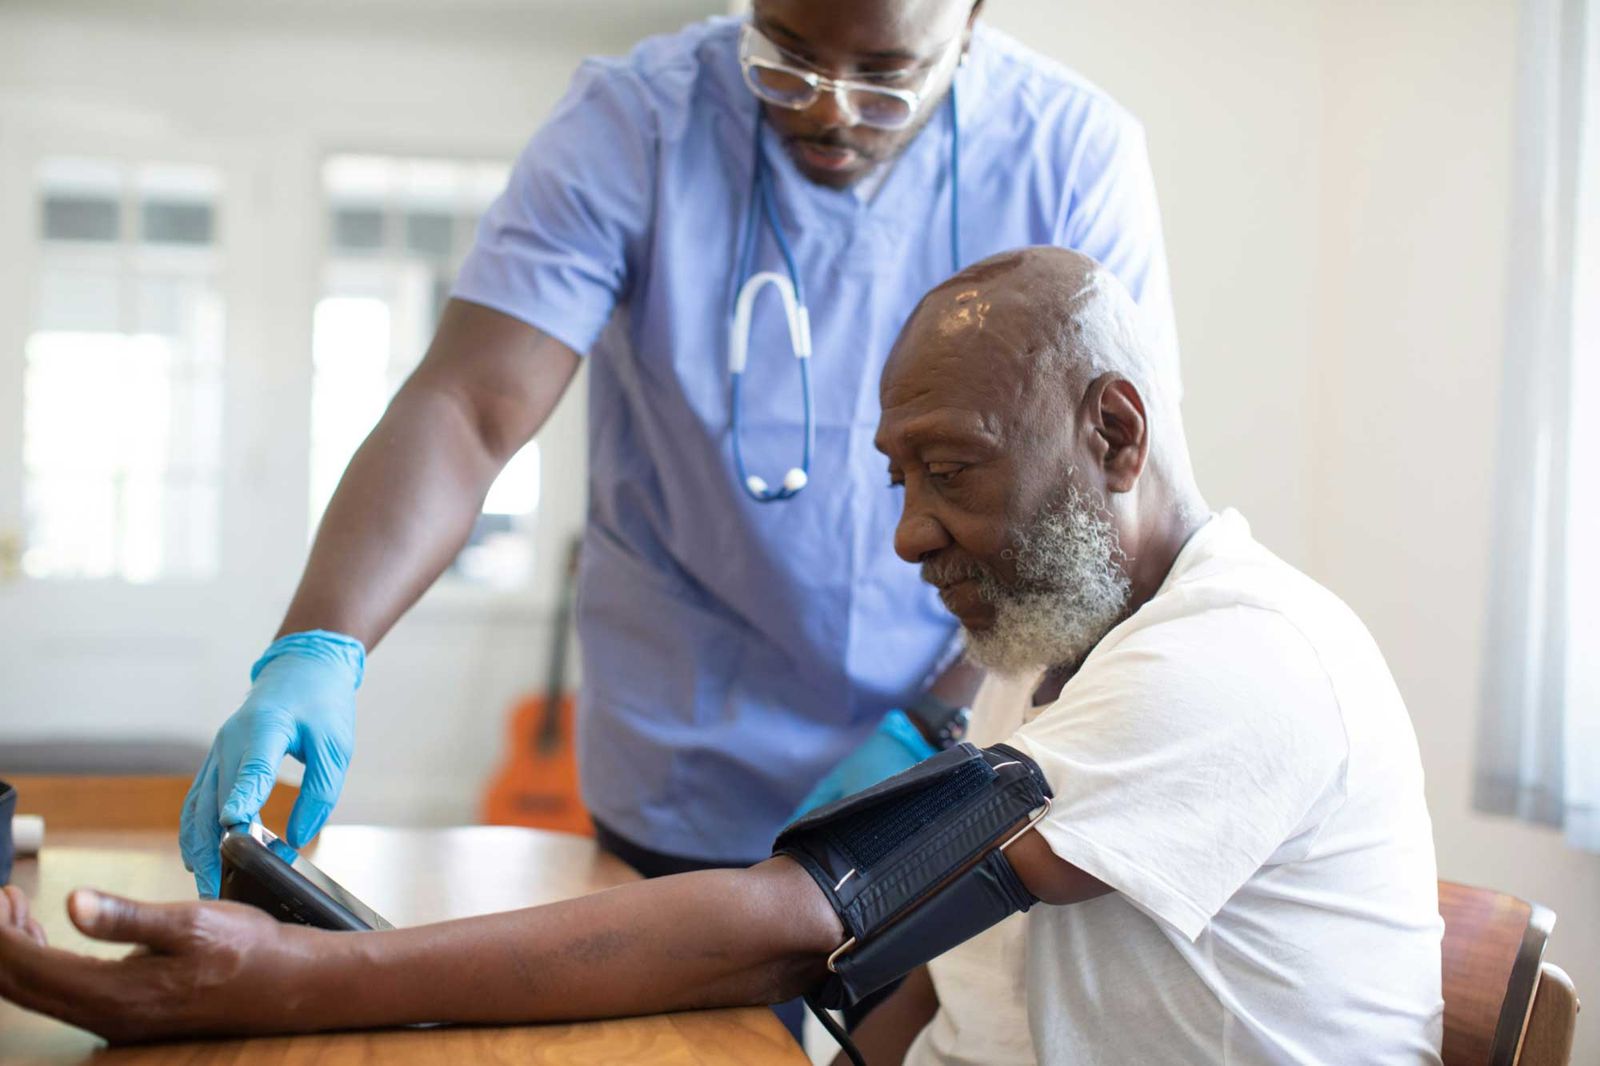
Blood pressure tends to climb with age, and the trajectory varies widely between populations—one international analysis found systolic pressure rising by anywhere from 1.7 to 11.6 mm Hg per decade between ages 30 and 64. A single reading is a snapshot; a trend is a story. Annual checks are the minimum for a man in his forties, and more frequent monitoring if a reading has ever been borderline.
2. Cholesterol
Lipid panels become more informative after 40, partly because the cumulative effect of years of LDL exposure starts to matter. Interestingly, the relationship between LDL and cardiovascular risk appears to strengthen with age rather than weaken—a long-term longitudinal study of men followed from age 50 to 82 found that the relative risk associated with LDL cholesterol actually increased as the men aged. A baseline lipid panel in your forties gives you and your clinician something to compare against later.
3. Blood sugar (glucose or HbA1c)
The American Diabetes Association recommends annual screening for type 2 diabetes starting at age 45 for average-risk adults, or earlier for those with risk factors such as excess weight or family history. The value of catching prediabetes is that it is often reversible through lifestyle change in a way that established diabetes is not. A fasting glucose or HbA1c is a cheap, simple test with high informational yield.
4. Prostate baseline
This is the number that requires the most nuanced conversation. For average-risk men, the U.S. Preventive Services Task Force recommends that those aged 55 to 69 discuss PSA screening with their clinician, weighing benefits against harms. But the conversation can reasonably start earlier—around 45—for men at higher risk, including Black men and those with a father or brother diagnosed with prostate cancer at a young age.
The key point is that a "baseline" does not automatically mean a biopsy or a diagnosis. It means establishing where you start, so that future changes are visible. An elevated PSA can come from many things besides cancer—infection, an enlarged prostate, even recent exercise. The first step after an elevated result is usually a repeat test, not a procedure.
What else deserves a mention
Beyond the core four, a few other items belong on the radar for men in their forties:
- Colorectal cancer screening. Guidelines generally recommend beginning at 45 or 50, depending on risk factors and the authority you follow. This is one of the few screenings that can actually prevent cancer by removing precancerous polyps.
- Hepatitis C and HIV. A one-time hepatitis C test is recommended for all adults ages 18 to 79, and a one-time HIV test for those 15 to 65, regardless of perceived risk.
- Vaccinations. Shingles vaccine at or after 50, tetanus booster every 10 years, and annual flu shots are part of the same preventive picture.
- Mental health. A good primary care visit should include questions about mood, stress, and sleep. Depression in men often presents as irritability or withdrawal rather than sadness, and it is a health issue, not a character flaw.
The conversation matters more than the checklist
The single most useful thing you can do is find a clinician who will look at your numbers in context—your family history, your habits, your waist circumference, your sleep, your stress. Screening is not a fixed menu. It is a conversation that gets refined over time.
If you are in your forties and it has been more than a year since your last physical, the honest first step is not a dramatic overhaul. It is a appointment. Bring your questions. Ask what your blood pressure was last time. Ask whether your cholesterol has moved. Ask what a reasonable prostate conversation looks like for you, given your risk profile.
The checkup you keep postponing is not a verdict. It is a baseline. And a baseline is the only thing that lets you see the drift before it becomes the problem.
This article is for general information and is not a substitute for medical advice. Screening recommendations vary by individual risk factors and should be discussed with a qualified clinician.